
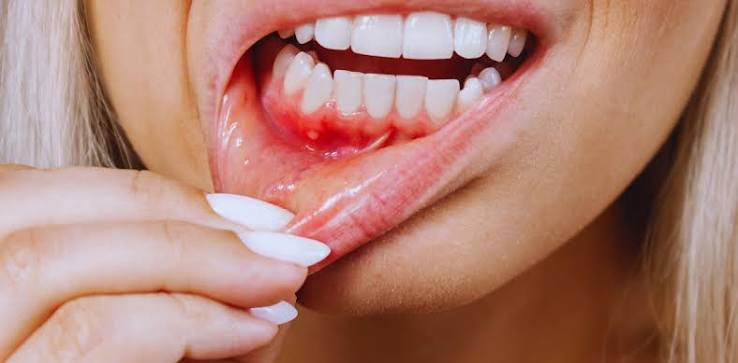
Key Takeaways
- According to CDC data, about 4 in 10 U.S. adults age 30 and older have some level of periodontitis. After age 65, the rate is closer to 60%.
- It’s usually painless early on.
- Gingivitis can be reversed. Periodontitis can’t, but professional care can slow it and keep it stable.
- Watch for bleeding when you floss, gums pulling back from your teeth, bad breath that won’t go away, and a partial denture that suddenly fits differently. Each of these is worth mentioning to a dentist.
- Treatment ranges from a deeper cleaning below the gumline to a referral to a periodontist. It’s usually followed by more frequent cleanings.
- One simple way to track your own gum health over time is to ask for your gum measurements at every visit.
Why Gum Disease Deserves More Attention on the South Shore
Ask most adults in Quincy, Braintree, or Weymouth what worries them about the dentist, and you’ll probably hear “cavities.” Gum disease rarely makes the list. But it’s one of the most common chronic conditions American adults live with, and together with tooth decay, it’s one of the two leading causes of tooth loss.
It’s also very good at staying quiet.
The CDC notes that periodontal (gum) disease can become serious before a person notices any symptoms. So by the time a tooth feels loose or a gum line looks lower, the damage underneath may have been building for years. Plenty of South Shore adults are busy with commutes, work, and family, and a checkup can get pushed back during a long New England winter. A disease that progresses slowly and without pain fits right into that gap.
What Gum Disease Actually Is
Gum disease isn’t one single condition. It’s a range, and where you fall on it matters a lot for what happens next.
Gingivitis Is the Early, Reversible Stage
Everyone has bacteria in their mouth, and those bacteria constantly form plaque, a sticky film on the teeth. When plaque sits along the gumline long enough, the gums get irritated. They turn red, puff up, and bleed easily when you brush or floss. In most cases, better home care plus professional cleanings can bring gingivitis back under control.
Periodontitis Involves the Bone
Plaque that isn’t removed hardens into tartar, also called calculus, and a toothbrush can’t get it off. Bacteria then work their way below the gumline and create pockets between the teeth and gums. Inside those pockets the inflammation continues, and the tissue and bone holding your teeth in place slowly break down.
Bone loss is the defining feature of periodontitis.
Here’s the part many people don’t realize: periodontitis can’t be reversed. Professional care can slow it, manage it, and keep it stable, which is why catching it early changes the whole conversation.
Who’s Most at Risk?
Age plays a big role. CDC data from 2009 to 2014 found that about 4 in 10 U.S. adults age 30 and older had some level of periodontitis, and the figure rose to roughly 60% among adults 65 and older. Men were affected more often than women, at about 1 in 2 compared with 1 in 3.
Those numbers have a hopeful side. People are keeping their natural teeth longer than earlier generations did, but more teeth over more years also means more gum tissue to look after.
Beyond age, these factors are linked with higher risk:
- Smoking. About 62% of adult smokers age 30 and older had periodontitis in that CDC data.
- Diabetes. Around 60% of adults with diabetes had periodontitis.
- Medications with oral side effects, such as dry mouth. This comes up often for people taking several prescriptions.
- Stress.
- Hormonal changes during pregnancy or menopause.
- Grinding, clenching, or crooked teeth.
- Genetics. Some people do everything right and still need closer monitoring.
Sound familiar? If two or three of these describe you, the cleaning schedule you’ve always followed may not be enough, and that’s a fair question to raise with your dentist.
How Gum Disease Affects More Than Your Mouth
The link with diabetes is the best established. The CDC says untreated periodontitis can make chronic conditions like diabetes worse, and people with diabetes are also more likely to develop gum disease in the first place. If you’re managing your blood sugar, your dentist and your physician are working on the same problem, whether or not they ever talk to each other.
You may also have seen headlines connecting gum disease and heart disease. Researchers have found associations between the two. Generally speaking, though, studies haven’t proven that gum disease directly causes heart problems, so it’s best treated as an open question rather than a settled fact.
Then there’s daily life. Advanced gum disease can make chewing painful, leave teeth sensitive, and shift the way your teeth come together. If teeth are eventually lost, replacing them with a bridge, an implant, or a denture means more appointments and more cost. Even dental implants depend on healthy gums and enough supporting bone, so gum disease usually has to be brought under control before implant work can start.
Signs You Shouldn’t Brush Off
Gum disease is often found during a routine exam rather than by the patient. Still, some signs are worth paying attention to:
- Gums that bleed when you brush or floss
- Red, swollen, or tender gums
- Gums that have pulled away from the teeth, which can make the teeth look longer
- Bad breath or a bad taste that won’t go away
- Loose or sensitive teeth
- A bite that feels different than it used to
- A partial denture that suddenly fits differently
That last one surprises people. If a partial that used to feel snug now rocks or rubs, the cause may be changes in the gums and bone underneath rather than a worn-out appliance.
Some gum problems can’t wait for your next cleaning, though. Swelling in the gums or face, a pimple-like bump on the gum, or a tooth that suddenly turns loose and painful can point to an abscess, so it’s worth finding a same day dentist who can examine the area promptly instead of waiting weeks for a routine opening. If swelling spreads quickly or makes it hard to breathe or swallow, that’s a medical emergency, so call 911 or go to the nearest emergency room instead.
What Treatment Usually Looks Like
Treatment depends on how far the disease has progressed, and no two mouths are quite the same. Generally speaking, though, it follows a few stages.
Measuring and Imaging
A dentist or hygienist uses a small probe to measure the space between each tooth and the gum. In healthy gums, those readings usually fall between 1 and 3 millimeters. Deeper readings can mean pockets are forming. X-rays show what’s happening to the bone underneath, which you can’t see in a mirror.
Deeper Cleaning and Ongoing Maintenance
Once pockets have formed, a routine cleaning usually isn’t enough. Scaling and root planing, often called a deep cleaning, removes tartar and bacteria from below the gumline and smooths the root surfaces. Some patients also need a prescription rinse or a medication placed directly under the gums. Advanced cases may require surgery from a periodontist.
Quincy Center Dental Associates, a general practice in Quincy Center led by Dr. Matthew Nguyen, a graduate of Tufts University School of Dental Medicine, describes a similar step-by-step approach. At preventive visits, its dentists measure and assess the gums and supporting bone and take diagnostic images when they’d help. When it’s appropriate, they recommend a deeper cleaning below the gumline, often followed by a more frequent recall schedule and changes to home care. If a case would be better managed by a periodontist, the practice says it will tell the patient and help coordinate that care.
One part of their approach stands out: they separate what needs treatment now from what can simply be monitored.
That distinction matters more than people think. A slightly deeper reading doesn’t always mean you need a procedure. A dentist who explains the difference gives you a much clearer picture of where you actually stand.
Questions Worth Asking at Your Next Cleaning
Most people get through a cleaning without asking a single question. But a few minutes of conversation can tell you far more about your gums than the polish ever will.
- What are my pocket readings, and have any changed since my last visit?
- Is this area something to treat now, or something to watch?
- Given my risk factors, how often should I come in?
- Would seeing a periodontist help in my situation?
- Could grinding or clenching be part of the problem? Dentists sometimes recommend a night guard when they see wear that points that way.
If you’re on Original Medicare, keep in mind that it generally doesn’t cover routine dental care like cleanings. Before you assume anything, check what your Medicare Advantage plan or separate dental coverage includes.
And if it’s been years since your last visit? That’s more common than you might think, and the best time to start again is simply the next appointment you can get.
Simple Habits That Protect Your Gums
None of this is complicated, which is part of what makes it easy to skip.
- Brush twice a day and floss once a day.
- See a dentist for a checkup at least once a year, or more often if you’re told to.
- If you smoke, quitting is one of the biggest things you can do for your gums.
- Work with your physician to keep diabetes well managed.
- Tell your dentist about any new medications, especially ones that leave your mouth dry.
If regular floss is hard to use, interdental brushes or a water flosser can help, particularly around bridges or crowded teeth. Your hygienist can show you which option makes sense for your mouth.
Frequently Asked Questions
Can gum disease be reversed?
Gingivitis, the early stage, can usually be reversed with good home care and professional cleanings. Periodontitis can’t be reversed because it involves bone loss, but treatment can slow it down and keep it stable.
How do I know if I have gum disease?
Common signs include bleeding when you brush or floss, red or swollen gums, receding gums, persistent bad breath, and loose teeth. Because early gum disease is often painless, a dental exam with gum measurements is the most reliable way to find out.
Is a deep cleaning the same as a regular cleaning?
No. A regular cleaning focuses on the tooth surfaces above the gumline. A deep cleaning, or scaling and root planing, removes tartar and bacteria from below the gumline and smooths the root surfaces.
How common is gum disease in adults?
According to the CDC, about 4 in 10 U.S. adults age 30 and older had some level of periodontitis between 2009 and 2014. Among adults 65 and older, the rate was about 60%.
Can gum disease cause tooth loss?
Yes. Periodontitis and tooth decay are the two leading causes of tooth loss, because advanced gum disease destroys the bone and tissue that hold teeth in place.
Does gum disease affect diabetes?
The relationship runs both ways. People with diabetes are at higher risk of gum disease, and untreated periodontitis can make diabetes harder to manage.
When should I see a periodontist?
A general dentist can manage many cases of gum disease. A referral to a periodontist, a dentist who specializes in the gums and supporting bone, is common when the disease is advanced, isn’t responding to treatment, or may need surgery.
Disclaimer: This article is for general educational purposes only and isn’t a substitute for professional dental or medical advice, diagnosis, or treatment. Talk with a licensed dentist or healthcare provider about your specific situation.
